
Do You Need a 3T MRI for Dental or Jaw Imaging?
Learn when dental and jaw problems usually need CBCT, panoramic X-ray, or intraoral imaging instead of 3T MRI, and when TMJ or soft-tissue MRI may make sense.
Key Takeaways
- Most tooth, implant, root, wisdom tooth, and canal questions need dental X-ray or CBCT, not 3T MRI
- MRI can help with TMJ disc, soft-tissue, marrow, infection-spread, and tumor-type questions
- CBCT and MRI answer different questions; a stronger magnet does not replace dental bone geometry
- Use existing scans first when they already answer the dental planning question
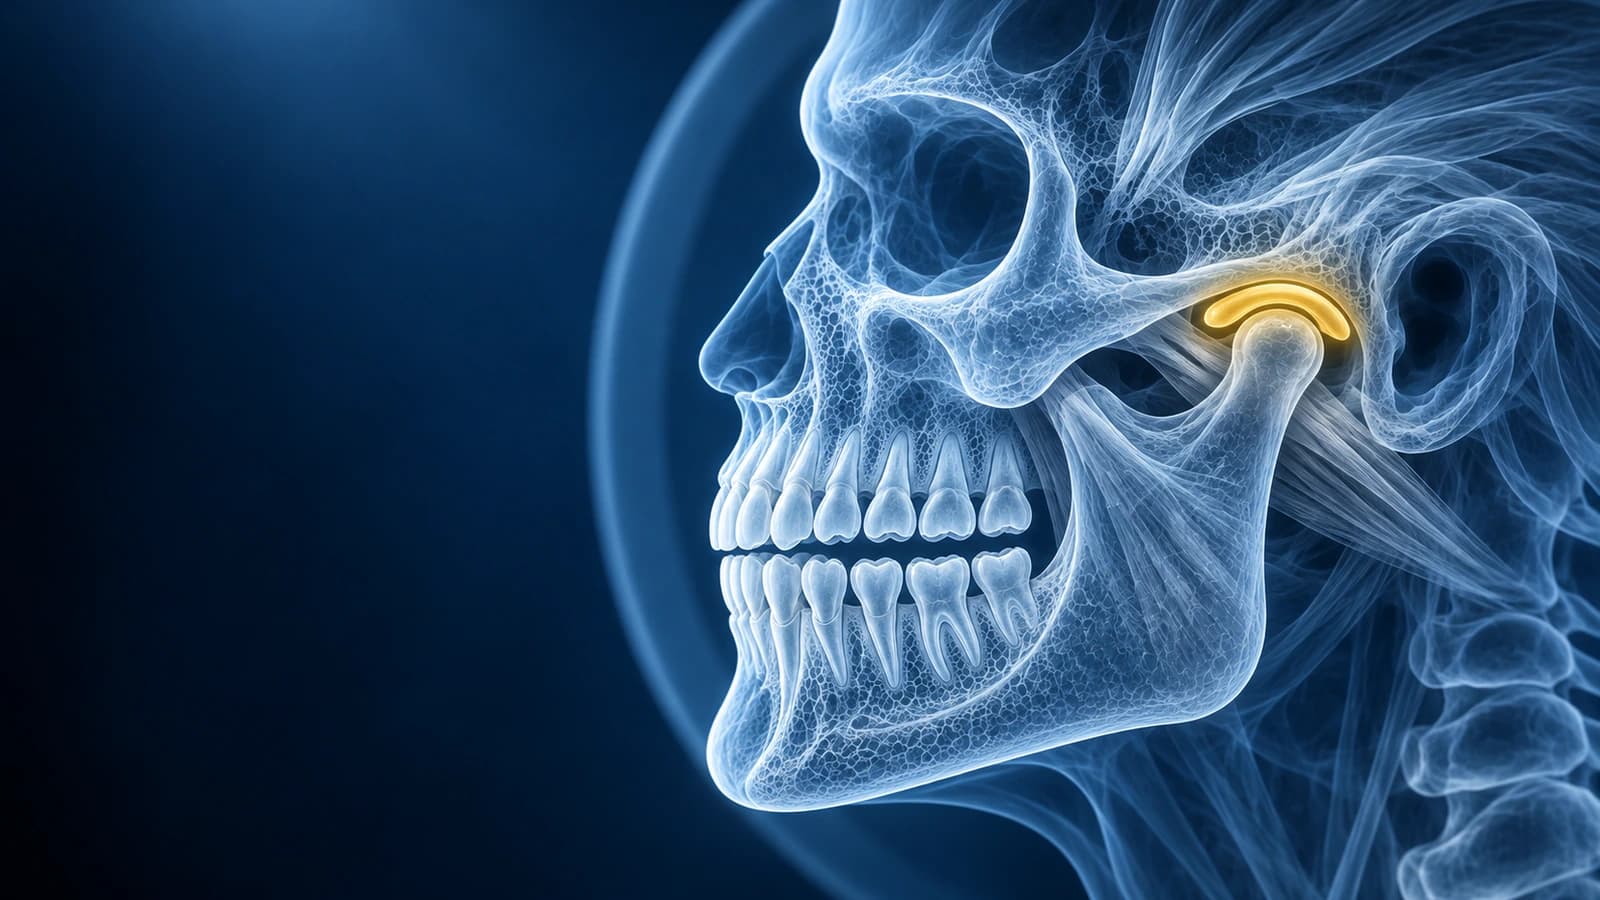
For most dental problems, 3T MRI is not the test you need. Teeth, implants, wisdom teeth, root fractures, jawbone structure, and canal relationships are usually evaluated with dental X-rays, panoramic X-rays, or CBCT. A stronger MRI magnet does not replace the geometry that dentists and oral surgeons need from CBCT.
MRI can still matter for jaw and TMJ questions because it shows soft tissue: disc position, joint inflammation, marrow, muscles, infection spread, and some tumor-like processes. The point is to avoid paying for 3T MRI when CBCT or a simple dental X-ray is the correct answer.
Quick Answer: When 3T Dental or Jaw MRI Is Worth Asking About
Ask about MRI for TMJ disc problems, unexplained jaw marrow changes, suspected soft tissue spread of infection, salivary or tumor-type questions, or complex pain where soft tissue is the missing piece. Do not pay for 3T MRI for routine implant planning, wisdom tooth position, root fracture, cavities, periodontal bone loss, or canal mapping.
When MRI Can Add Value for Jaw and TMJ Problems
- TMJ disc displacement, joint effusion, synovitis, or internal derangement
- Jaw marrow, muscle, soft-tissue, or infection-spread questions not answered by CBCT
- Suspected cystic, salivary, nerve, or tumor-type processes where soft tissue matters
- Complex post-treatment pain when the clinical question is not simply tooth or bone geometry
When You Probably Do Not Need 3T
- Dental implant planning, where CBCT is usually the correct 3D bone map
- Wisdom tooth position, root shape, and mandibular canal relationship questions
- Root fracture, periapical lesion, periodontal bone loss, or endodontic planning
- Routine cavities, bitewing findings, or intraoral dental problems
- Repeating a recent CBCT just because a 3T MRI sounds more advanced
3T MRI vs CBCT for Dental Decisions
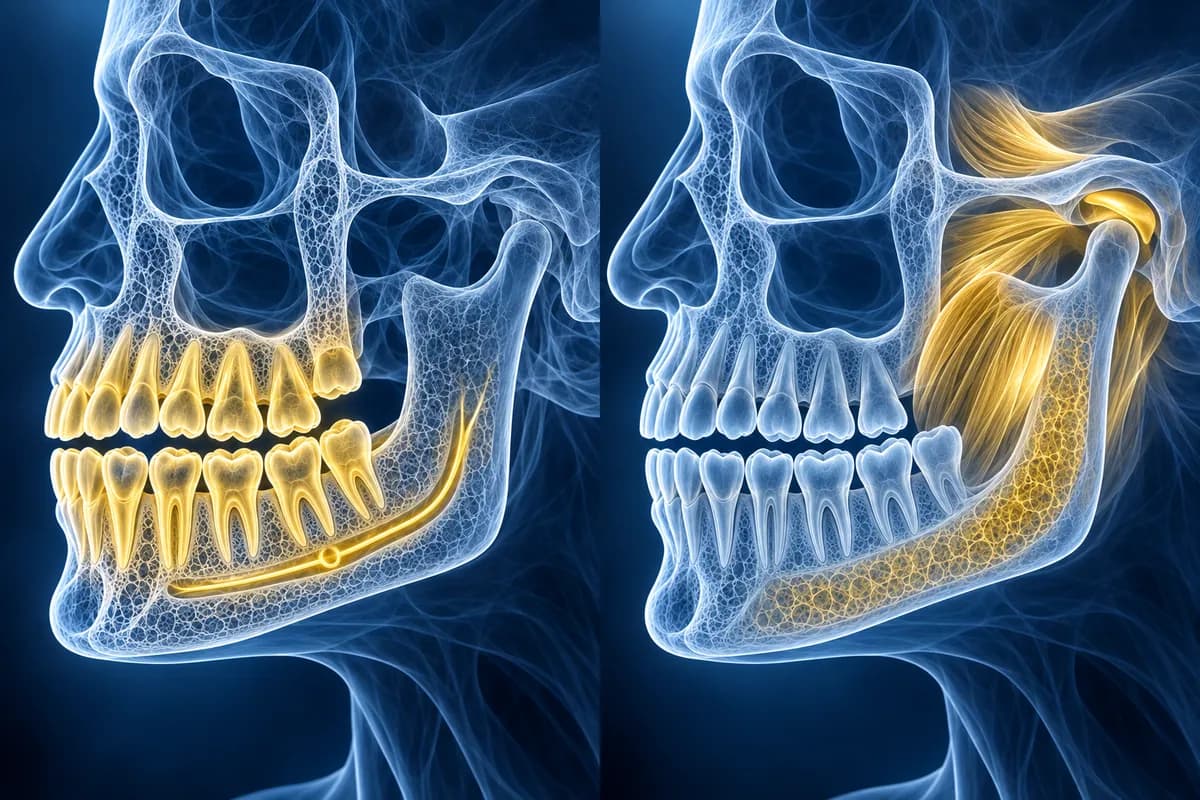
CBCT is built for teeth and jawbone geometry. MRI is built for soft tissue, marrow, and joint discs. If the decision is implant position, wisdom tooth risk, root fracture, or canal mapping, compare your options in our CBCT vs panoramic X-ray guide.
Frequently Asked Questions
Do I need 3T MRI for dental implant planning?
Usually no. Dental implant planning typically needs CBCT because it shows jawbone width, height, canal location, sinus anatomy, and 3D bone geometry. MRI is not a substitute for that planning map.
When is MRI useful for jaw or TMJ problems?
MRI is useful when the question is TMJ disc position, joint inflammation, marrow, muscle, soft-tissue spread of infection, nerve involvement, or tumor-like tissue, not routine tooth or implant geometry.
Can 3T MRI replace dental CBCT?
No. CBCT is usually the better tool for teeth, roots, jawbone, implants, and wisdom tooth anatomy. MRI can complement CBCT when soft tissue or TMJ detail is the missing question.
Sources
- Tomas X, Pomes J, Berenguer J, et al. MR imaging of temporomandibular joint dysfunction: a pictorial review. Radiographics. 2006;26(3):765-781.
- Ahmad M, Hollender L, Anderson Q, et al. Research diagnostic criteria for temporomandibular disorders (RDC/TMD): development of image analysis criteria and examiner reliability for image analysis. Oral Surg Oral Med Oral Pathol Oral Radiol Endod. 2009;107(6):844-860.
- Larheim TA, Abrahamsson AK, Kristensen M, Arvidsson LZ. Temporomandibular joint diagnostics using CBCT. Dentomaxillofac Radiol. 2015;44(1):20140235.
- Tyndall DA, Price JB, Tetradis S, et al. Position statement of the American Academy of Oral and Maxillofacial Radiology on selection criteria for the use of radiology in dental implantology with emphasis on cone beam computed tomography. Oral Surg Oral Med Oral Pathol Oral Radiol. 2012;113(6):817-826.
Related Articles
Learn how to understand dental CBCT views, slices, MPR planes, tooth roots, jawbone, sinuses, mandibular canal, and common report terms.
Compare dental CBCT and panoramic X-ray for wisdom teeth, implants, jaw cysts, root problems, orthodontics, radiation tradeoffs, and second opinions.
Understand how CBCT helps evaluate impacted wisdom teeth, root shape, mandibular canal proximity, maxillary sinus relationship, and extraction planning questions.
Related Conditions
Understand your imaging before your next appointment
CBCT or CT from a CD, folder or ZIP, a panoramic X-ray, or an intraoral 3D scan (STL).
Free to open and preview, no account needed. An optional AI report from $10 explains your images in plain language, with questions for your doctor.
Your raw files stay on this device. Only rendered images and minimal context are sent when you request an AI report.
Medical Disclaimer: This page is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. AI-generated analysis may contain errors. Always consult a qualified healthcare professional for medical decisions. Full Disclaimer